Your dream smile abroad + private Medellin conciergeFree Veneers Abroad Guide for U.S. patients

Zirconia Veneers: Strengths, Trade-offs, and Where They Fit

Zirconia is a dental ceramic known for strength, while its opacity and translucency vary by formulation and thickness. Learn what the material can and cannot tell you, where it may fit, which evidence limits matter, and what a dentist should verify before a plan is compared.

Compare the questions before you choose a clinic or plan a trip.

  • Clinical evidence with attribution and caveats
  • Candidacy signals a dentist should review
  • Material authenticity questions to ask any clinic
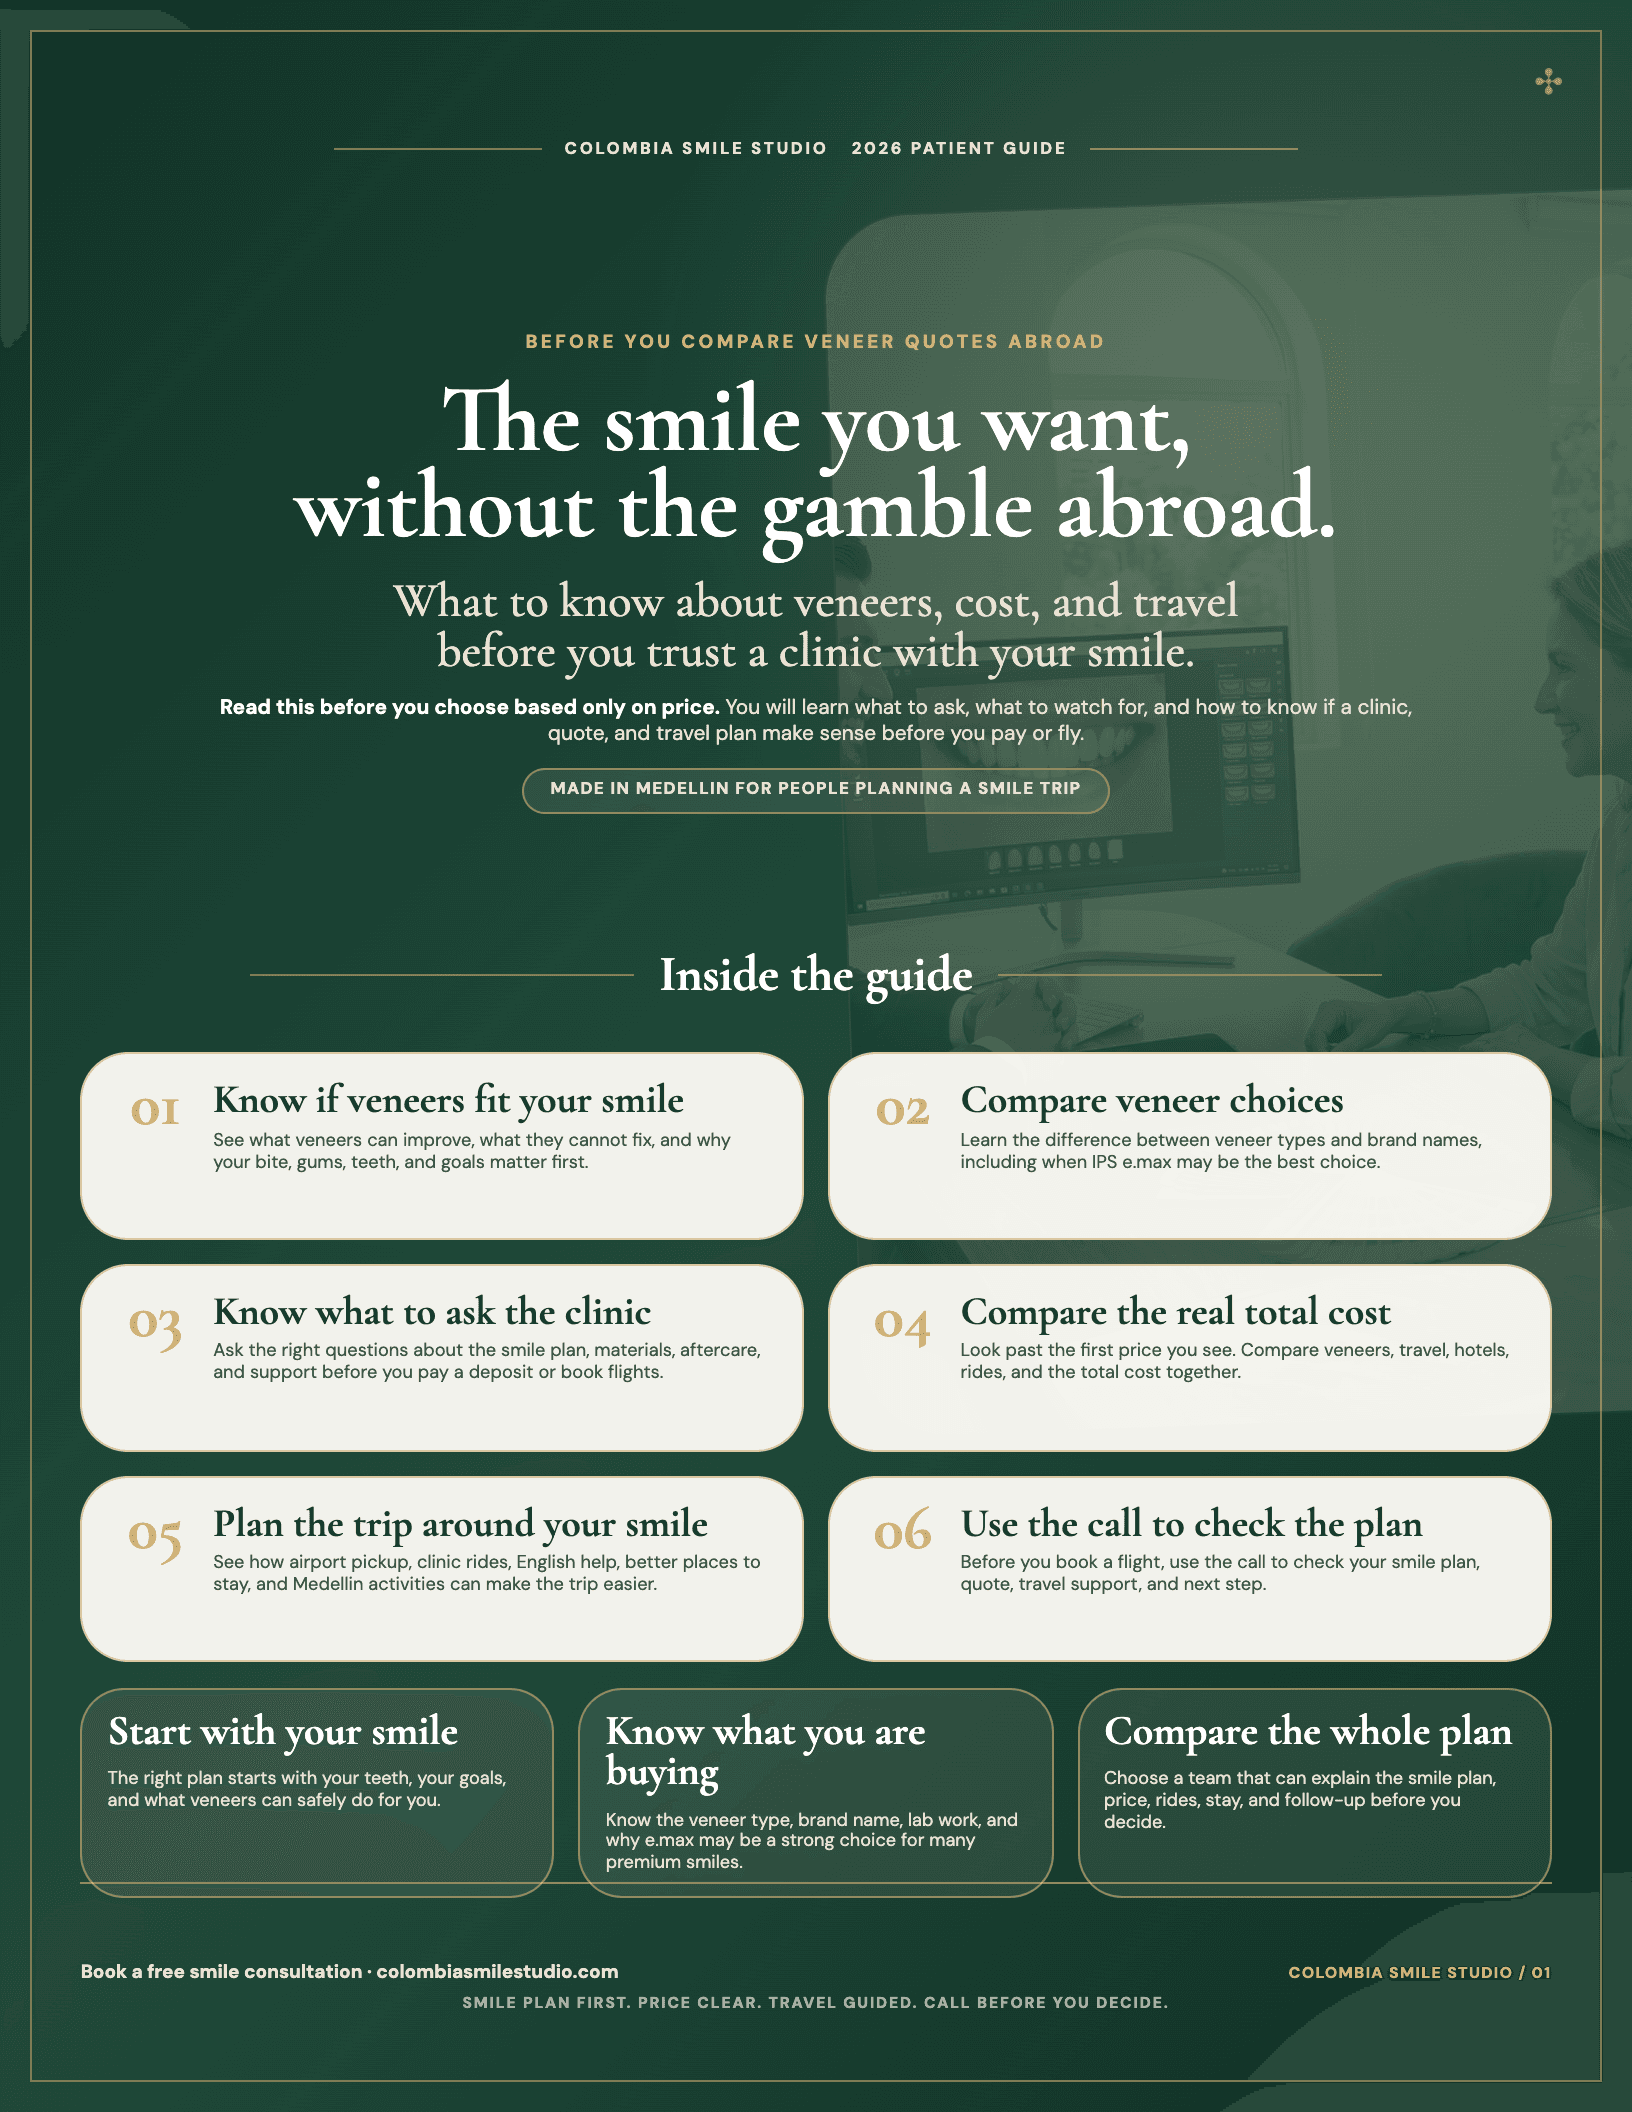
Cover of the free Colombia Smile Studio Veneers Abroad Guide
Adult discussing zirconia veneer considerations with a dentist in a generic dental consultation setting.
Material identity and optics

What zirconia veneers are, and why the formulation matters

Zirconia is a polycrystalline ceramic used for dental restorations. A zirconia veneer covers the visible front surface of a selected tooth and is bonded as part of an individual treatment plan. The material is known for strength, but the word zirconia does not identify one universal formulation or appearance.

Different zirconia formulations balance strength, opacity, and translucency differently. Thickness, shade, surface finish, and the underlying tooth color also affect how the restoration handles light. That is why zirconia should not be described as automatically opaque, automatically natural-looking, or universally better than another ceramic.

A veneer-specific laboratory study found that the monolithic zirconia specimens it tested were less translucent than lithium disilicate specimens, that thickness affected translucency, and that the masking result varied by zirconia material. This is material evidence from an in-vitro study, not proof of a clinical result for every formulation or patient.

Some zirconia formulations can provide more masking than more translucent glass ceramics, which may matter when underlying color must be managed. The same opacity can be an optical trade-off when the design goal calls for greater light transmission. The treating dentist and laboratory must connect the chosen formulation to the tooth foundation, preparation, shade, thickness, surface finish, and intended design.

The material name does not decide which teeth should receive veneers, how much preparation may be appropriate, how the restorations will be bonded, who will fabricate them, or what written follow-up applies. Ask for the manufacturer, exact product line or tier, planned restoration on each tooth, and documentation that matches the material actually proposed.

The porcelain veneers guide owns the broader porcelain category, while the veneers hub explains the treatment family. Read the separate Emax veneer guide and feldspathic veneer guide for those material paths. For a buyer decision across materials, use the Emax, zirconia, and composite comparison rather than treating this page as a winner verdict.

Three planning decisions

How a zirconia veneer question becomes a tooth-by-tooth plan

A material name should follow a clinical and design decision, not replace one. The dentist, laboratory, and patient need a connected plan for the restoration, optical goal, fabrication, bonding, records, and follow-up before treatment begins.

01

Decide what each tooth needs

A dentist first reviews oral health, existing restorations, tooth structure, available enamel, tooth position, underlying shade, and the bite. The responsible question is whether a veneer, another restoration, or no restorative treatment fits each tooth after an individual examination.

02

Match masking and light handling to the design

The proposed formulation, thickness, shade, and surface finish should be considered alongside the underlying tooth color and the intended smile design. More masking is not automatically better, and more translucency is not automatically better. The choice should serve the case-specific appearance and tooth-restoration plan.

03

Verify the material and workflow

Ask which dentist is responsible for preparation, try-in, and bonding, which laboratory is making the restorations and where it is located, which zirconia manufacturer and product line or tier is proposed, what material records will be provided, and what happens if adjustment, repair, or follow-up is needed after returning home.

Candidacy and dentist review

Where zirconia may fit, and what a dentist must review

Zirconia veneers may be considered in specific cases, but the material name cannot establish candidacy. A dentist must first decide whether a veneer or another path fits each tooth after examining oral health, existing dental work, tooth structure, enamel, position, underlying shade, and the bite.

Strength and masking can matter when the restoration needs to manage underlying color or a demanding tooth-restoration situation. Those qualities do not make zirconia universally better. Formulations differ, and a more opaque option may look less enamel-like than a more translucent ceramic in some designs.

The dentist also has to weigh preparation, the enamel available for bonding, the proposed formulation and thickness, light handling, surface treatment, bonding approach, bite forces, habits, laboratory execution, and follow-up. A fixed online rule cannot resolve those connected decisions for an individual patient.

Adult discussing case-specific zirconia veneer considerations with a dentist beside a tooth model and secured shade guide.

What the dentist reviews

A zirconia veneer question should bring these checks together:

Tooth foundation
The condition and structure of each tooth, existing restorations, oral health, underlying shade, tooth position, and the amount and quality of enamel available for bonding.
Masking and appearance plan
The color that may need to be preserved, changed, or masked, the proposed zirconia formulation and thickness, and how shade, translucency, shape, texture, and neighboring teeth affect the intended appearance.
Bite, bonding, and follow-up
Bite forces, clenching, grinding, edge contact, the planned surface treatment and bonding approach, laboratory responsibilities, and the written maintenance, adjustment, repair, and follow-up path.

The American Dental Association's veneer guide explains the general veneer process and why treatment planning belongs to a dentist. The exact restoration, preparation, material, and bonding plan remains case-specific. A material description or search query cannot determine treatment for a patient.

Evidence, verification, and value

What the evidence can and cannot tell you about zirconia veneers

Reliable long-term clinical evidence for zirconia laminate veneers remains limited. A systematic review and meta-analysis found that comparable long-term zirconia laminate-veneer data were not available. That evidence gap does not prove failure, but it does mean a fixed zirconia veneer lifespan or long-term guarantee would go beyond the evidence.

White-coated dentist hands presenting brand-neutral ceramic samples beside a tooth model on a clean clinical surface.

Laboratory material studies can help explain opacity, translucency, masking, and the effect of thickness. They cannot establish how long a veneer will last for an individual patient or prove that one formulation will produce a particular appearance in the mouth.

The material name alone also does not establish preparation quality, surface treatment, bonding, laboratory execution, or follow-up. Value depends on how those parts fit the tooth-by-tooth plan and on which responsibilities are documented before treatment.

Ask any clinic to identify the zirconia manufacturer and exact product line or tier, the planned restoration and material for each tooth, the laboratory and its location, who reviews the design, how the material is documented, who performs the final bonding, and what written follow-up responsibilities apply. Generated material imagery on this page is conceptual and is not proof of authentic zirconia, clinic inventory, a laboratory relationship, or a clinical result.

Zirconia veneer cost can vary with the restoration on each tooth, tooth count, material tier, laboratory, smile design, preparation and bonding needs, written inclusions, aftercare, and whether follow-up may require travel. This page publishes no zirconia treatment price.

Comparing veneer prices in Colombia requires more than a country label or headline number. First identify whether the proposed restoration uses composite resin or porcelain or ceramic. For a ceramic plan, distinguish a named material such as Emax from an unbranded ceramic tier. Then identify the lab by name and location and confirm the aftercare path for polishing, adjustments, repairs, or remakes after you return home, including whether travel may be required. This is market-level comparison guidance, not a Colombia Smile Studio price quote. Use the all-in cost model to compare like with like.

A country name alone does not establish the quality or safety of any individual treatment plan. What decides that is the treatment itself: the restoration and material class (composite resin vs porcelain; Emax vs unbranded ceramic), the lab and where it is, the treating dentist's credentials, the aftercare and adjustment path once you are home, and the written warranty or remake policy. Weigh those against the quote, not headline price alone.

Read how long veneers last for the full evidence discussion and its limits. Use the Emax, zirconia, and composite comparison for the buyer decision. Use the all-in veneer cost model for detailed cost guidance.

Zirconia can represent good value when the restoration, formulation, appearance plan, laboratory, bonding, written inclusions, and follow-up fit the patient. Value does not come from a material name, an unsupported lifespan claim, or the smallest headline number. A dentist must first decide whether a veneer and the proposed material are appropriate for the teeth and bite.
Free planning guide

Compare zirconia veneer questions with one guide

Use the guide to organize restoration, material, clinic, cost, laboratory, preparation, bonding, and aftercare questions before you evaluate a veneer treatment trip.

Patient questions

Common questions about zirconia veneers

Use these answers to understand the material, appearance, and fit questions worth taking to a dentist. They are educational and cannot determine an individual plan without an examination.

What are zirconia veneers?

Zirconia veneers are ceramic restorations made from zirconium dioxide and bonded over the visible surface of selected teeth. Zirconia is known for strength and can be more opaque than some glass ceramics, but its appearance varies by formulation, thickness, shade, and surface finish. The material name alone does not determine candidacy, preparation, tooth count, or the final design.

How do zirconia veneers differ from porcelain?

Some zirconia formulations are more opaque and can mask underlying color more readily than more translucent porcelain materials. Porcelain can handle light differently, which may support a more enamel-like appearance in some plans. Formulation, thickness, shade, surface finish, the underlying tooth color, and the intended result all affect the choice. A broader buyer comparison belongs on the Emax, zirconia, and composite comparison page.

Are zirconia veneers a good choice?

Zirconia veneers can be a reasonable material choice when masking underlying tooth color is a priority and the dentist considers its strength useful for the plan. The trade-off is that a more opaque formulation may look less enamel-like than a more translucent porcelain option in some cases. Suitability depends on the teeth, bite, preparation, material formulation, lab work, and design goals, so the material name alone does not establish value or fit.

Free planning guide

Ready to plan your dream smile abroad?

Get the free Veneers Abroad Guide and see the full picture: real costs, clinic-standard questions, and what to ask before you ever book a flight.